Treatment Planning for Pancreatic Cancer Patients: From Diagnosis to Preliminary Cost Estimate
A pancreatic cancer diagnosis rarely arrives with a clear next step attached. Patients get a stage, maybe a resectability status — and a lot of decisions land on them at once.
This overview walks through pancreatic cancer treatment planning: confirming the diagnosis, mapping the options, and reaching a realistic cost figure before any commitment is made.
Diagnosis Decides Which Options Are on the Table
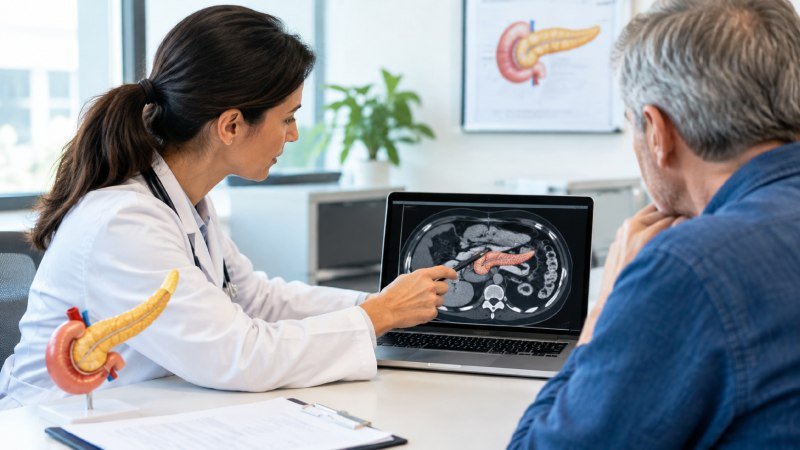
Pancreatic cancer diagnosis has to be precise before a plan means anything. Vague early symptoms — blood sugar shifts, weight loss, abdominal discomfort — often delay detection, so imaging and biopsy do the real work of confirming type, location, and stage.
A tumor’s resectability decides which pancreatic cancer treatment options are even relevant.
| Approach | Typical role | Delivery |
| Surgery (Whipple procedure) | Removable tumors, curative intent | Operating room, ICU stay |
| Chemotherapy | Before/after surgery, or as primary treatment | Systemic, cycles over months |
| Radiation | Local control, symptom relief | Targeted beams, often with chemo |
| Targeted therapy | Tumors with a specific mutation (BRCA1/2) | Drug matched to genetics |
| Dendritic cell / TACE / ablation | When standard protocols aren’t enough | Interventional, localized |
Pancreatic cancer treatment almost always combines more than one row above. Surgical volume matters too — a team doing the Whipple procedure dozens of times a year handles complications differently than one that does it occasionally.
Not One-Size-Fits-All
Treatment planning for pancreatic cancer hinges on resectability, tumor genetics, and how the patient is tolerating things. A borderline tumor might respond to chemotherapy first, opening up surgery that wasn’t possible at diagnosis. None of this gets decided by one specialist alone — it takes a tumor board.
This is where a second opinion for pancreatic cancer earns its place — confirming “inoperable” really means inoperable, and every current approach was considered. A pancreatic cancer second opinion matters most when the first assessment came without full molecular testing.
A thorough pancreatic cancer medical case review checks resectability, genetic markers, prior treatment response, and overall condition together, before recommending anything.
Considering Treatment Abroad
A tumor called inoperable at home isn’t always inoperable. Sometimes it’s just inoperable at that hospital. Patients look into pancreatic cancer treatment abroad for that reason mostly — a high-volume center classifies the same scan differently — but also for access to a pancreatic cancer treatment program that hasn’t reached their home country yet, or simply because they want one more qualified look before signing off on anything. Cancer treatment in Germany tends to pair standard protocols with methods still investigational elsewhere.
None of that means booking a flight and figuring it out on arrival. A treatment program before travel should already be settled — workup done, tumor board weighed in — before the trip even gets booked. Skip that step and the cost shows up later, not in money but in time: extra scans nobody flagged, records that turn out half-complete, a plan that has to be rebuilt mid-visit. International pancreatic cancer patients run into this more than they’d expect.
Getting to a Cost Estimate
Treatment cost for pancreatic cancer varies enormously with the approach. A preliminary cost estimate, and any cost estimate before treatment abroad, should reflect the actual proposed plan rather than a generic price list. Pancreatic cancer treatment cost abroad depends on surgical complexity, drug protocols, and how many interventional sessions the case needs — clear only once the case review is done.
Booking Health Coordination Through the Process
Here’s where Booking Health coordination actually starts: reading through what a patient already has, and figuring out what’s real once the local options have run out. Not the top name on a ranking. Oncology clinic selection, done properly, means matching a specific diagnosis to a physician who’s actually treated that presentation before.
What comes after that is less glamorous but matters just as much. A case manager stays on for up to a year. The budget gets fixed before treatment starts, not adjusted halfway through. Medical travel support covers the paperwork, the translations, the scheduling — the parts that eat a family’s time without teaching them anything. Complication insurance sits underneath all of it. And the actual medical calls? Those stay with the doctors treating the case, as they should.